Chronic headaches often leave patients and healthcare providers searching for answers beyond conventional treatments. For nurses assessing a client with persistent migraines or tension-type pain, the temporomandibular joint (TMJ) may hold critical clues. This often-overlooked joint connects the jaw to the skull, yet dysfunction here can trigger referred pain radiating to the temples, forehead, or even the back of the head—mimicking primary headache disorders. When a nurse prepares to evaluate a TMJ, the initial interaction sets the stage for accurate diagnosis, patient comfort, and effective communication.
The TMJ’s intricate link to headaches stems from its proximity to muscles, nerves, and blood vessels that influence cranial pain pathways. Muscle tension in the masseter or temporalis, for instance, can compress nerves and restrict blood flow, exacerbating migraines or cervicogenic headaches. Yet many clients arrive at assessments with misconceptions—assuming TMJ evaluations involve invasive procedures or that their pain is purely psychological. A nurse’s role extends beyond physical examination; it includes educating patients on what to expect, debunking myths, and fostering an environment where clients feel empowered to describe their symptoms honestly. Proper preparation can transform a routine assessment into a pivotal step toward relief.
Assessing Temporomandibular Joint Dysfunction in Clients with Chronic Headaches: Anatomical, Physiological, and Clinical Insights
The temporomandibular joint (TMJ) is a complex hinge connecting the jawbone to the skull, yet its dysfunction often remains underdiagnosed in clients presenting with chronic headaches. For nurses working with clients who have a history of migraines, tension-type headaches, or cervicogenic headaches, recognizing the anatomical and physiological links between TMJ dysfunction and cephalic pain is critical. The TMJ’s proximity to cranial nerves, cervical spine, and masticatory muscles creates a pathway for referred pain, muscle tension, and neurovascular disturbances that can mimic or exacerbate primary headache disorders. A systematic assessment of the TMJ, including patient history, physical examination, and observation of associated signs, allows nurses to identify potential contributors to headache etiology, improve diagnostic accuracy, and guide interdisciplinary referrals. This section explores the anatomical relationships between the TMJ and headache triggers, physiological mechanisms underlying TMJ-related pain, and clinical tools—such as comparative tables, flowcharts, and screening checklists—to enhance assessment precision in nursing practice.
Anatomical Relationship Between the TMJ and Headache Triggers
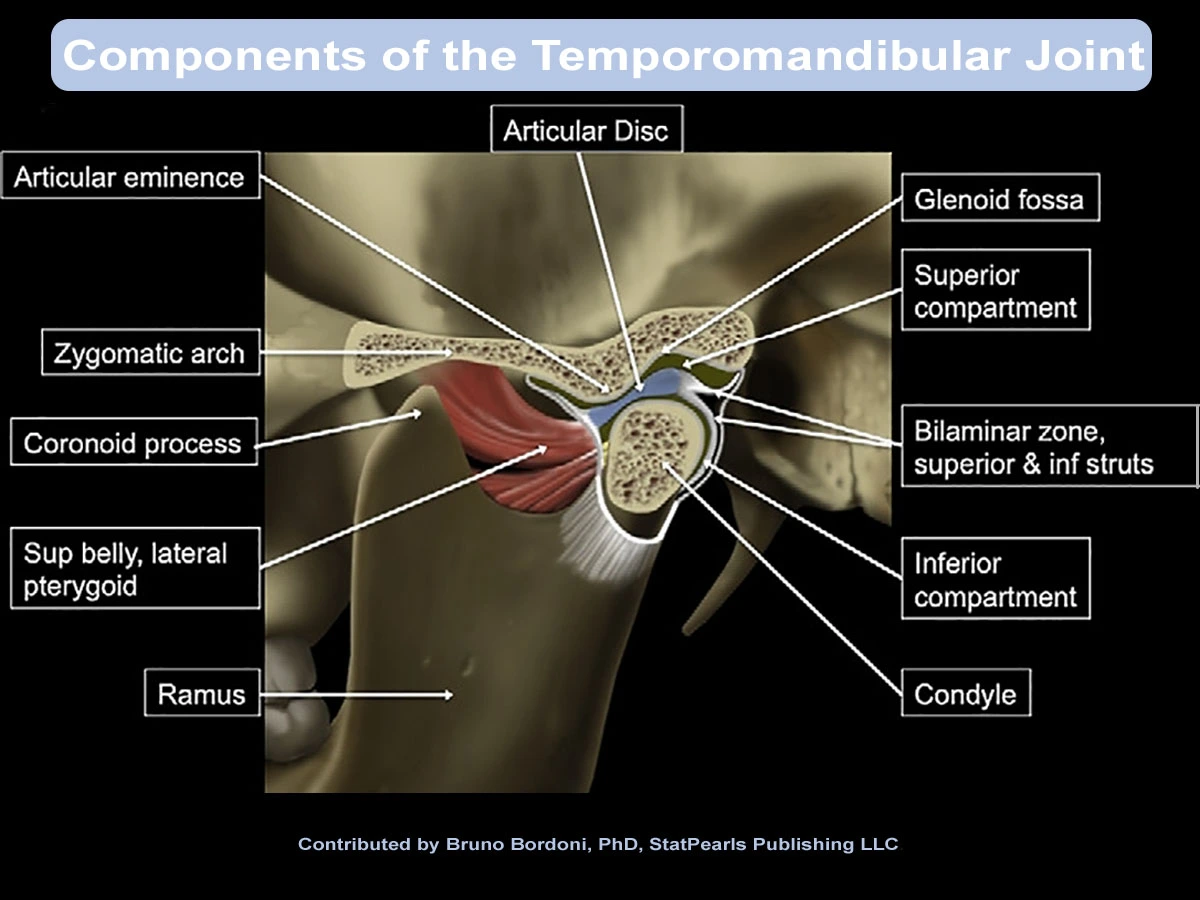
The TMJ is situated anterior to the ear, where the mandibular condyle articulates with the temporal bone of the skull. Surrounding structures, including the masseter muscle (responsible for jaw closure), temporalis muscle (assisting in elevation and retraction), lateral pterygoid muscle (critical for jaw protrusion and depression), and medial pterygoid muscle, contribute to mandibular movement and stability. Dysfunction in these muscles or the joint itself can lead to muscle hyperactivity, joint inflammation, disc displacement, or arthritic changes, all of which may radiate pain to the temporal, frontal, or occipital regions of the head.
The auriculotemporal nerve (a branch of the mandibular division of the trigeminal nerve, CN V3) innervates the TMJ and surrounding tissues, creating a direct neural pathway for pain referral. When the TMJ is affected, sensory input from the joint can be perceived as pain in the temporal area, forehead, or even behind the eyes, mimicking tension-type headaches. Additionally, cervical spine referral patterns often overlap with TMJ-related pain due to shared innervation from the greater occipital nerve (C2) and third occipital nerve (C3), which can further complicate differential diagnosis.
Referred pain mechanisms also play a role. For example, tension in the temporalis muscle may irritate the supraorbital nerve, while dysfunction in the lateral pterygoid muscle can compress the auriculotemporal nerve, leading to preauricular pain, earaches, or even migrainous symptoms. The masseter muscle, when in spasm, can refer pain to the temporomandibular region and crown of the head, a pattern frequently observed in clients with bruxism or clenching habits.
A detailed diagram description of the TMJ’s anatomical layout would highlight:
The mandibular condyle resting in the mandibular fossa of the temporal bone, separated by an articular disc.
The lateral ligament and sphenomandibular ligament stabilizing the joint.
The superficial temporal artery and middle meningeal artery in proximity, explaining how vascular disturbances (e.g., inflammation or compression) may contribute to vascular headaches.
The digastric muscle and stylohyoid muscle, which, when tense, can pull on the hyoid bone and indirectly affect cranial nerve function.
Understanding these anatomical connections allows nurses to recognize how TMJ dysfunction can trigger or worsen headaches through mechanical stress, nerve irritation, or vascular changes.
Physiological Mechanisms Linking TMJ Disorders to Migraines, Tension-Type, and Cervicogenic Headaches
The relationship between TMJ disorders and headaches is mediated by neurogenic, vascular, and musculoskeletal pathways. Each headache subtype exhibits distinct physiological interactions with TMJ dysfunction:
1. Migraines and TMJ Dysfunction
Migraines are often associated with trigeminal nerve activation, and the TMJ’s close anatomical relationship with the mandibular division (V3) of this nerve provides a plausible link. Studies suggest that TMJ inflammation or disc displacement may trigger trigeminal autonomic cephalalgias (TACs) through substance P release and neurogenic inflammation, mimicking migrainous symptoms. Additionally, bruxism (a common TMJ-related behavior) is linked to increased cortisol levels, which can lower the migraine threshold in susceptible individuals.
2. Tension-Type Headaches and Muscle Tension
Chronic tension in the masticatory muscles (masseter, temporalis) and cervical muscles (splenius capitis, levator scapulae) leads to myofascial pain, a primary contributor to tension-type headaches. The TMJ’s role in mastication means that prolonged clenching, grinding, or malocclusion can perpetuate muscle hypertonicity, creating a viscous cycle of pain and compensatory movements that exacerbate headaches.
3. Cervicogenic Headaches and TMJ-Cervical Spine Connection
The upper cervical spine (C1-C3) shares common innervation with the TMJ via the greater and lesser occipital nerves. Dysfunction in the TMJ can lead to altered head posture, increased cervical lordosis, or suboccipital muscle tension, all of which contribute to cervicogenic headaches. Furthermore, referred pain from the TMJ can converge with cervical facet joint pain in the occipital and parietal regions, complicating diagnosis.
4. Vascular and Neurogenic Contributions
Vascular: Inflammation in the TMJ region can affect nearby arteries (e.g., superficial temporal artery), potentially contributing to vascular headaches or even temporal arteritis-like symptoms.
Neurogenic: Peripheral sensitization in the TMJ may lead to central sensitization in the trigeminal nucleus caudalis, a brainstem region involved in both TMJ pain and migraine pathophysiology.
A 2018 study published in Cephalalgia found that 40-70% of clients with chronic migraines exhibited TMJ dysfunction, suggesting a significant overlap in pathophysiology. Nurses must recognize that TMJ-related headaches often respond differently to treatment than primary headaches, emphasizing the need for targeted assessments.
Comparative Analysis: TMJ-Related Headaches vs. Primary Headaches
Understanding the distinguishing features between TMJ-related headaches and primary headaches (e.g., migraines, cluster headaches) is essential for accurate diagnosis. Below is a comparative table outlining key differences:
Pain aggravated by palpation of TMJ or masticatory muscles.
Clicking, popping, or crepitus in the jaw.
Limited mouth opening (<40 mm) or deviation upon opening.
Tenderness in preauricular area or along sternocleidomastoid.
Trigger Factors
<
Pre-Assessment Preparation: Nurse’s Role in Client Education and Environment Setup
Effective TMJ assessment begins long before palpation or examination—it starts with meticulous preparation and client education. A nurse’s ability to guide the client through positioning, manage expectations, and create a comfortable environment directly influences the accuracy of findings and the client’s willingness to participate. Poor preparation can lead to misdiagnosis, heightened anxiety, or even avoidance of future assessments. This section outlines the structured approach nurses should adopt to ensure clients are physically and psychologically prepared for TMJ evaluation, emphasizing clear communication, cultural sensitivity, and a client-centered approach.
Step-by-Step Instructions for Client Positioning and Preparation
The physical setup for TMJ assessment requires deliberate attention to detail to minimize discomfort and maximize diagnostic accuracy. Clients with chronic headaches may already experience heightened sensitivity, making proper preparation critical.
Positioning the Client
The nurse should instruct the client to adopt a seated upright position with their back supported against the chair. This alignment prevents muscle strain in the neck and shoulders, which can exacerbate TMJ-related discomfort. The client’s head should be lightly supported—either by the chair’s headrest or the nurse’s guidance—to avoid unnecessary tension. If the assessment requires the client to open or close their mouth, a neutral head position (aligned with the spine) ensures consistency in palpation.
Removing Restrictive Items
Before proceeding, the nurse must identify and address items that could interfere with the assessment:
Tight collars or scarves should be loosened to prevent compression of the jaw and neck muscles.
Dentures or partials should be removed if they are not securely fitted, as they can alter joint movement and mask underlying dysfunction.
Jewelry or accessories near the jawline (e.g., necklaces, earrings) should be temporarily removed to avoid obstruction or discomfort during palpation.
Preparing for Discomfort
Clients often associate medical assessments with pain, even when procedures are non-invasive. The nurse should proactively manage expectations by stating:
> "During this assessment, you may feel mild pressure or hear a slight clicking sound in your jaw. These sensations are normal and indicate the joint is moving as expected. If you experience sharp pain or extreme discomfort, please let me know immediately so we can adjust."
This script reassures the client while differentiating between expected sensations (pressure, clicking) and red flags (sharp pain, radiating discomfort). The nurse should also explain that the assessment involves gentle touch only, with no instruments penetrating the skin.
Calibrating Client Expectations and Addressing Common Fears
Anxiety about TMJ assessments often stems from misconceptions about pain, invasiveness, or the purpose of the examination. Nurses play a pivotal role in normalizing the process and demystifying the assessment for clients.
Key Areas to Address
Pain Misconceptions: Many clients fear the assessment will be painful, assuming it involves deep tissue probing or manipulation. The nurse should clarify that TMJ palpation is superficial and controlled, focusing on surface landmarks like the joint line, muscles of mastication (e.g., masseter, temporalis), and ligaments.
Invasiveness Concerns: Clients may worry about the assessment being "too personal" or intrusive. Emphasizing that the procedure is external and non-invasive—comparable to checking pulse points or joint mobility—helps alleviate discomfort.
Purpose Clarification: Some clients may not understand why their TMJ is being assessed, especially if headaches are their primary symptom. The nurse should explain the anatomical connection between TMJ dysfunction and headaches, citing studies that link TMJ disorders to referred pain patterns in the temporal, frontal, and occipital regions.
Script Template for Nurse-Client Communication
To standardize education, nurses can use the following structured script during pre-assessment discussions:
1. Purpose of the Assessment
"Today, we’re assessing your temporomandibular joint to understand if it’s contributing to your headaches. The TMJ connects your jawbone to your skull, and problems here can sometimes cause pain that radiates to your head or face. This will help us determine if physical therapy, lifestyle changes, or further testing might be beneficial."
2. Expected Sensations vs. Red Flags
*"You might feel:
Gentle pressure as I press on certain areas—this is normal and helps me locate the joint.
A slight clicking or popping when you move your jaw—this is common and usually harmless.
You should NOT feel:
Sharp or stabbing pain during palpation.
Numbness or tingling in your face or arms.
If you experience any of these, let me know right away."*
3. Communication During Assessment
*"Your feedback is very important. If something feels:
Uncomfortable but tolerable, say ‘discomfort.’
Too intense, say ‘stop’ or ‘adjust.’
Painful, we’ll pause immediately to discuss next steps."*
4. Reassurance
"This assessment is quick, painless for most people, and won’t require you to do anything strenuous. Afterward, we’ll review what we found and how it might relate to your headaches."
Common Client Misconceptions and Nurse Responses
Misunderstandings about TMJ assessments can hinder cooperation and lead to inaccurate findings. Below is a table outlining four prevalent misconceptions, along with nurse clarifications, educational resources, and follow-up actions to ensure clients leave with correct information.
Misconception
Nurse’s Clarification
Educational Resource to Recommend
Follow-Up Action
"TMJ assessments hurt because they involve deep tissue work."
"The assessment focuses on the joint and surrounding muscles with light touch—similar to how a dentist checks your bite. We’re not digging deep or manipulating the joint forcefully."
Video: "What Does a TMJ Exam Feel Like?" (American Academy of Orofacial Pain)
Demonstrate palpation on the nurse’s own TMJ to show the pressure level.
"If my TMJ clicks, it means I need surgery."
"Clicking is very common and doesn’t always indicate a problem. It often occurs when the joint disc moves slightly during function. Surgery is rarely needed unless there’s severe pain, locking, or limited movement."
Infographic: "TMJ Clicking: Myths vs. Facts" (National Institute of Dental and Craniofacial Research)
Article: "When to Worry About Jaw Clicking" (Healthline)
Ask the client: "Have you noticed any locking or pain with the clicking?" to assess severity.
"This assessment will take too long and is unnecessary."
"The assessment typically takes 5–10 minutes and is a key part of ruling out TMJ-related causes for your headaches. Skipping it might mean missing a treatable condition."
Short Read: "The Link Between TMJ and Chronic Pain" (Cleveland Clinic)
Explain how findings will guide treatment plans (e.g., physical therapy, oral appliances).
"I’ll need to keep my mouth open the whole time."
"You’ll only need to open or close your mouth when guided—usually just a few movements to check for smooth function. Most of the assessment involves resting your jaw naturally."
FAQ Page: "What to Expect During a TMJ Exam" (American Dental Association)
Show the client the range of motion required (e.g., opening to 2–3 fingers’ width).
Ensuring Privacy, Comfort, and Optimal Environment
A well-prepared environment reduces client anxiety and improves the nurse’s ability to conduct a thorough assessment. Physical comfort and privacy are foundational to building trust and obtaining accurate responses.
The assessment of a client’s TMJ for headache-related dysfunction is not just a clinical procedure—it is an opportunity to bridge gaps between symptoms and solutions. By providing clear instructions, addressing fears, and engaging patients as active participants, nurses can uncover hidden triggers and improve diagnostic accuracy. Understanding the physiological connections between TMJ dysfunction and headaches, coupled with thoughtful communication, empowers both patients and providers to navigate complex pain management strategies. In an era where misdiagnosis remains common, these foundational steps ensure that no potential cause is overlooked—and that every client leaves the assessment with clarity, hope, and a pathway to relief.

 Understanding the distinguishing features between TMJ-related headaches and primary headaches (e.g., migraines, cluster headaches) is essential for accurate diagnosis. Below is a comparative table outlining key differences:
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Cloudpbx.